Aunque pueda contener afirmaciones, datos o apuntes procedentes de instituciones o profesionales sanitarios, la información contenida en el blog EMS Solutions International está editada y elaborada por profesionales de la salud. Recomendamos al lector que cualquier duda relacionada con la salud sea consultada con un profesional del ámbito sanitario. by Dr. Ramon REYES, MD
Niveles de Alerta Antiterrorista en España. Nivel Actual 4 de 5.
👉Seguimos añadiendo documentos de consulta rápida de la Agencia Formación de SEMERGEN con el fin de aportarte información concisa y clara de uso ágil. ¡COMPARTE
🆕¡NUEVOS!
📗Manejo de la ansiedad
📗Manejo de las complicaciones crónicas de la diabetes mellitus tipo 2
¿Qué debes considerar al configurar una zona de aterrizaje?
La zona de aterrizaje debe tener un mínimo de 100’X100', de día o de noche. El lugar de aterrizaje debe estar libre de obstáculos, peligros y escombros. El terreno debe ser firme, y evitar, si es posible, pendientes superiores a cinco grados. Se deben evitar los lugares de aterrizaje con arena blanda o tierra, pero se pueden mojar como último recurso.
Puede resultar difícil para los pilotos ver pequeñas obstrucciones desde el aire. Un estudio del sitio debe incluir electricidad aérea, teléfono u otras obstrucciones; antenas, edificios o árboles altos, con un intento de eliminar o limitar cualquiera de estas obstrucciones del lugar de aterrizaje. Si alguno de los objetos está presente en el lugar de aterrizaje, será importante notificar a la tripulación de vuelo de su presencia. Es posible que quieran que busque una ubicación diferente.
Marque la zona de aterrizaje. Para hacer esto, use conos con peso o coloque vehículos de emergencia en la esquina de la zona de aterrizaje con los faros hacia adentro para formar una X.
Si existen vientos fuertes, será útil informar a la tripulación de vuelo sobre la dirección y velocidad del viento.
Asegúrese de que todo el personal, transeúntes y vehículos no esenciales estén al menos a 200 pies de la zona de aterrizaje.
El personal que opere cerca de la zona de aterrizaje debe estar preparado para vientos fuertes y ruido. Los socorristas deben contar con todo el EPP durante el despegue y el aterrizaje, incluidos cascos con correas para la barbilla, protección para los oídos y protectores faciales u otra protección para los ojos.
What should you consider when setting up a Landing Zone?
The landing zone should be a minimum of 100’X100', day or night. The landing location should be free of obstacles, hazards, and debris. The site should be firm, and avoid slopes greater than five degrees, if possible. Soft sand or dirt landing sites should be avoided, but can be wet down as a last resort.
It can be difficult for pilots to see small obstructions from the air. A survey of the site should include, overhead power, telephone, or other obstructions; antennas, buildings, or tall trees, with an attempt to remove or limit any of these obstructions from the landing location. If any of the objects are present at the landing location, it will be important to notify the flight crew of their presence. They may want you to find a different location.
Mark the landing zone. To do this, use weighted cones or position emergency vehicles at the corner of the landing zone with headlights facing inward to form an X.
If strong winds exist, it will be helpful to inform the flight crew of the wind direction and speed.
Ensure that all nonessential personnel, bystanders, and vehicles are at least 200ft from the landing zone.
Personnel operating near the landing zone should be prepared for high wind and noise. Responders should have all PPE in place during take-off and landings, to include helmets with chin straps, ear protection, and face shields or other eye protection.
Velocidad de impacto de vehículos y severidad de heridas en peatones.Fuente: Literature review on vehicle travel. Speeds and pedestrian injuries (1999)
A la mayoría de las personas nos gusta viajar, conocer nuevos lugares, nuevas ciudades, nuevas culturas y personas, respirar otros aires, es por eso que siempre estamos esperando las vacaciones o el momento exacto para subirnos a un medio de transporte ya sea por aire, tierra o mar, eso no importa, el simple hecho de salir de tu vida cotidiana es un placer.
Pero no todo es diversión y placer al viajar, también tenemos que tener en consideración los riesgos o accidentes que se pueden presentar al momento de tomar un medio de trasporte, a pesar de que cada año se mejora la seguridad de estos para prevenir accidentes, reduciendo el índice de mortalidad para el beneficio del cliente, debemos de ser precavidos y tener en cuenta que la seguridad es primero.
La forma más fácil de evitar un accidente durante un viaje, es escoger correctamente el asiento que ocuparás al desplazarte de un lugar a otro y es por eso que a continuación te mostraremos cuales son los asientos más seguros que puedes ocupar al tomar los 7 medios de trasporte más usados, después de haber revisado algunas estadísticas de muchos accidentes.
El moderno sistema de medio de transporte es uno de los mayores avances de la humanidad
El avance tecnológico ha revolucionado al mundo como lo vemos hoy, desde el transporte aéreo teniendo la facilidad de cruzar océanos en horas, lo cual era imposible hace 100 años, hasta el tren bala que puede viajar más de 300 km/h.
Por más modernos y seguros que sean los medios de transporte, a veces pueden ocasionar un accidente.
Desde luego siempre aparece el miedo de subirnos a un vehículo o transporte para viajar, pensando que podemos sufrir una tragedia, pero es necesario saber que las victimas mortales son pocas, debido a que cada año se mejora la seguridad en los medios de trasporte para prevenir accidentes, sin embargo, no está de más saber que asiento tomar en los distintos medios de transporte para viajar más seguro y sufrir el menor daño posible.
Barco
La forma más segura de transportarte en un barco es tomar los camarotes que se encuentran en cubierta o los más cerca de ella, debido a que la parte superior es la última en hundirse, todo lo contrario de los camarotes que se encuentran en la parte inferior del barco debido a que se encuentra más cerca del agua y del casco.
Auto
Si optas por tener un viaje en automóvil debes de considerar que el asiento más inseguro es el del copiloto debido a que durante un choque de frente con otro automóvil el conductor intenta por instinto esquivar el vehículo poniendo en riesgo al copiloto, por otra parte los asientos más seguros se encuentran detrás del conductor ya que durante un choque de frente son los que menos reciben daño.
Avión
Si nos ponemos a pensar no existe muchas posibilidades de sobrevivir durante un accidente aéreo, aunque se considera uno de los medios de transporte más seguros del mundo, aun así para tratar de salir ileso muchos expertos piensan que tomar los asientos de la parte posterior de un avión tienes más posibilidad de sobrevivir que tomar los de la parte frontal.
Minivan
La forma más segura de tratar de salir ileso durante un viaje en una minivan es sentarte en los asientos que se encuentran en dirección contraria al movimiento, ya que si se frena súbitamente existe menos posibilidad que te golpees la cabeza con el respaldo, sin embargo, los asientos más inseguros se encuentran cerca de las puertas y ventanas ya que durante un accidente se pueden cortar con los vidrios si estos revientan, de igual forma el asiento del copiloto es conveniente evitarlo.
Tren
Toma en cuenta que los vagones más afectados al viajar en tren son los que se encuentran en los extremo, ya sea por descarrilamiento o colisión, es por eso que te recomendamos tomar los vagones que se encuentran a la mitad de este, usualmente es entre el 5to y el 7mo vagón dependiendo el que tu elijas y así tomar los asientos que se encuentran a la dirección del movimiento del tren ya que los que están perpendiculares al eje largo del vagón son menos seguros.
Tranvía
Se tiene que considerar que no en todo el mundo se maneja por el mismo lado, ya sea izquierda o derecha, es por eso que te recomendamos buscar los asientos del medio en dirección al movimiento para tu seguridad, por otro lado los asientos que se encuentran cerca de las ventanas evita tomarlos pues es probable que salgas lastimado por algún vidrio roto en una colisión.
Autobús
Los asientos más seguros al viajar en un autobús tratando de salir ileso se encuentran en la parte derecha y en medio del pasillo debido a que se ubican más lejos del tráfico que va en dirección contraria, sabiendo esto debes de tomar en cuenta que los asientos más peligrosos se encuentran en las dos primeras filas debido a que durante un choque de frente pueden salir heridos al romperse el parabrisas o por algún pedazo o astilla que se desprenda del otro coche, de la misma manera evita tomar los asientos de atrás debido a que son igual de peligrosos si ocurre un choque trasero, los asientos que se encuentran cerca de las ventanas y puertas, tienen más posibilidad de sufrir alguna herida por un vidrio quebrado durante el choque.
Las fases de descomposición del cuerpo humano El cuerpo humano pasa por diversos procesos químicos una vez que ha perdido la vida. Uno de los principales procesos que sucede instantáneamente después de la muerte es el rigor mortis. Luego sucede la descomposición, que tienen cinco fases: El fresco: dura una semana y los tejidos cambian de color. El hinchamiento: los gases producidos por las bacterias inflan el cuerpo, lo que puede hacer que se hinche y se deforme. La putrefacción activa: las bacterias continúan descomponiendo los tejidos blandos y se produce un fuerte olor a descomposición. La putrefacción avanzada: los tejidos blandos se han descompuesto casi por completo y el cuerpo comienza a esqueletizarse. El seco o de los restos: todo el tejido blando ha desaparecido y solo queda el esqueleto. "En estas etapas también ocurren diversos procesos químicos y biológicos. El cuerpo sin vida se verá afectado por diversas sustancias, como la cadaverina y la putrescina, que son producidas por el mismo cuerpo, las cuales ocasionarán que el organismo se descomponga rápidamente", describe Marcela Lorena Fierro Villalba, en el artículo 'Mujer y tigre: estudio del organismo humano después de la muerte'. Le puede interesar: (Aparecen cadáveres abandonados de 6 bebés en entrada de cementerio en Santo Domingo) El tiempo que tarda un cuerpo en descomponerse depende de varios factores, como la temperatura ambiente, la humedad, la causa de la muerte y la presencia de insectos y otros animales carroñeros. El proceso puede tomar de meses hasta años, pero es el camino natural después de la muerte.
España: Se introduce la figura del PARAMEDICO "MEDIC" en las Fuerzas Armadas
Las Fuerzas Armadas introducen la figura del paramédico en sus unidades de combate
Harán su trabajo en lugares aislados o situaciones hostiles cuando no pueden llegar los médicos militares. La figura ya existe en EEUU o Reino Unido.
Los paramédicos serán una realidad en lasFuerzas Armadas españolas. Así lo ha aprobado este viernes el Consejo de Ministros, introduciendo una figura que ya existe en ejércitos como los de Estados Unidos, Reino Unido o Israel. Habrá militares con la suficiente formación médica como para atender a sus compañeros heridos graves en lugares aislados o en situaciones hostiles, cuando los médicos militares no pueden llegar a la zona.
A estos militares se les dotará de una formación con tres niveles (básico, medio y avanzado) y se les instruirá para saber cómo actuar en situaciones específicas proporcionando asistencia, lo que favorecerá la supervivencia y posterior evacuación a las formaciones sanitarias de tratamiento en unos momentos que son realmente importantes y en los que no están presentes los equipos sanitarios de soporte vital avanzado.
El nivel de capacitación acreditado por el correspondiente certificado habilitará a estos paramedicos militares para actuar únicamente en escenarios operativos, en ausencia de personal facultativo o en apoyo del mismo, y de acuerdo con lo ratificado por España en las organizaciones internacionales de seguridad y defensa. Es decir, en ningún momento se utilizarán para sustituir el trabajo de los médicos militares.
España: Se introduce la figura del PARAMEDICO "MEDIC" en las Fuerzas Armadas
La atención sanitaria en escenarios operativos se centrará en atender las lesiones que producen un mayor número de muertes en combate, como las hemorragias masivas, el neumotórax a tensión o la obstrucción de la vía aérea y las actuaciones que resulten indicadas en situaciones de aislamiento, en especial en ambiente hostil o de bajas masivas.
Estos paramédicos tendrán dependencia funcional de los oficiales del Cuerpo Militar de Sanidad de las especialidades fundamentales de medicina y enfermería, en el ejercicio de sus cometidos y apoyo a la atención sanitaria. La creación de esta figura no significará en ningún caso que los militares españoles dejen recibir los cursos de soporte vital básico que forman parte de la instrucción militar.
Social Media is a buzz with the latest reports of an American tourist being attacked while visiting a resort in Punta Cana. The story seems to be evolving by the minute with new information that has some people casting a bit of doubt on the story. The comments on Facebook have ranged from thoughtful concern to downright stupidity.
Over the last year there were several crimes reported on the North Coast involving tourists and ex-pats. Unfortunately a few of those incidents were violent in nature and even ended with fatalities. Without question each and every one of these incidents needs to be investigated, factually reported and broadcasted to the general public. Unfortunately the current trend on the various Facebook Groups and the American media is to take a poorly translated news clip and then start random conjecturing. This usually ends up with a bunch of disparaging remarks labeling the Dominican Republic as an “unsafe” place to visit or to live.
There needs to be some context and real data added to the discussion. So here is our take.
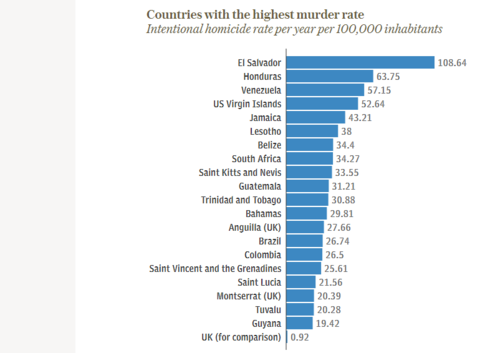
FACT: Crime exists in every single corner of the world. Chicago, Toronto, Cancun, Los Angeles, London, New York, Orlando, St. Thomas, Nassau, San Juan, Freeport, Key West…..deep breath - Honolulu, Cozumel, Rio, Rome, Vancouver, Washington DC, New Orleans, St. Croix, San Juan and Jamaica to name a few. All of these places are major tourist destinations and they ALL have one thing in common. Higher violent crime rates than ANY of the tourist destinations in the Dominican Republic. The US Virgin Islands of St. Thomas, St. John and St. Croix….have the fourth highest murder rate in the world, according to a study done by the United Nations Office on Drugs and Crime (UNODC). Only El Salvador, Honduras and Venezuela have more murders per capita. Yet we rarely see news stories blasting away about the security concerns involved with a trip to the VI’s…
The 2018 global peace index has the Dominican Republic listed as the 73rd most dangerous country in the world. That’s below the United States, China, Russia, Thailand, Mexico, Israel, Brazil, Egypt and pretty much anywhere in Africa, the Middle East and South America.
highest-murder-rate.png
Statistically speaking you have much higher chance of being robbed at gunpoint on your way into Disney World than you do walking to the beach in Sosua or Cabarete. If one were to take the time and fully read every news story regarding crime involving tourists or expats in the Dominican Republic (we did), you’d be hard pressed to find a report of violent crime against a tourist while they were out doing touristy things. Almost all of the violent crime reported on the North Shore involves either drugs and/or prostitution. All very real and concerning. To label the Dominican Republic as an unsafe place to live is statistically inaccurate and very misleading.
The Dominican Republic is as safe as YOU make it. If you come here to enjoy the beach with your family there is very little chance that you will be the victim of a violent crime. The majority of the crime in this country is petty theft and crimes of opportunity. If your visiting with the intent of finding love in all the wrong places or looking to participate in the evening pharmaceutical trade than your odds go way up. But this is true for any tourist destination in the known universe. So when JoeyG from Boise starts his Facebook rant about how dangerous the DR is…. take it with a grain of salt. We have over 6,000,000 tourists visit our country per year - the statistics don’t lie, the Dominican Republic is one of the SAFEST destinations for tourist in the entire Caribbean.
Mascarilla: Europa se abre a "relajar" su uso entre completamente vacunados
El ECDC publica una evaluación sobre el uso de la mascarilla y el distanciamiento social tras la vacunación completa
Israel ha decidido eximir el uso obligatorio de la mascarilla en lugares cerrados, y para finales de mayo ha fijado el término definitivo de su uso. Esta medida se ha podido implementar gracias a su campaña de vacunación (más del 50 por ciento de la población vacunada con dos dosis). En la búsqueda de este mismo escenario, el Centro Europeo para el Control y la Prevención de Enfermedades (ECDC, por sus siglas en inglés), se ha abierto a “relajar” el uso de la mascarilla entre individuos completamente vacunados, según lo han establecido en un nuevo documento de recomendaciones para el control de la pandemia.
“A medida que avanza el despliegue de la vacunación, es alentador tener recomendaciones basadas en evidencia de que la inmunización puede permitir lentamente la relajación de intervenciones como el uso de mascarillas y el distanciamiento social. Si bien la relajación de las medidas de protección debe hacerse gradualmente y sobre la base de evaluaciones cuidadosas de los riesgos involucrados, confiamos en que una mayor cobertura de vacunación tendrá un impacto positivo y directo para volver a la vida normal ”, ha explicado Andrea Ammon, directora del ECDC.
En este contexto, las recomendaciones establecidad por la ECDC sobre el uso de la mascarilla y el distanciamiento social tras los beneficios de la vacunación completa basados en los siguientes puntos:
Cuando las personas con pauta completa de vacunación se encuentran con otras personas en las mismas condiciones de inmunización, el distanciamiento social y el uso de mascarilla se pueden relajar.
Cuando un individuo no vacunado o individuos no vacunados del mismo hogar o burbuja social se encuentran con individuos completamente vacunados, el distanciamiento social y el uso de la mascarilla se pueden relajar si no hay factores de riesgo de enfermedad grave o menor efectividad de la vacuna en cualquiera de los presentes.
Al rastrear contactos, los contactos vacunados que han estado expuestos a un caso confirmado deben seguir siendo tratados de acuerdo con las directrices existentes del ECDC. Sin embargo, las autoridades sanitarias pueden considerar la posibilidad de realizar una evaluación de riesgos caso por caso y, posteriormente, clasificar algunos contactos completamente vacunados como contactos de bajo riesgo. Los factores que deben tenerse en cuenta en tales evaluaciones incluyen, por ejemplo, la situación epidemiológica local en términos de variantes circulantes, el tipo de vacuna recibida y la edad del contacto. También se debe considerar el riesgo de transmisión a personas vulnerables por el contacto.
Los requisitos para las pruebas y la cuarentena de los viajeros (si se implementan) y las pruebas periódicas en los lugares de trabajo pueden no aplicarse o modificarse para las personas completamente vacunadas siempre que no exista una circulación de las variantes inmunitarias de escape o un nivel muy bajo (en la comunidad del país de origen, en el caso de viajeros).
En el contexto epidemiológico actual europeo, en espacios públicos y en grandes reuniones, incluso durante los viajes, la mascarilla debe mantenerse independientemente del estado de vacunación de las personas.
What have we learned about oxygen? The dangers of too much O2
It was 0635. Larry and Adriane always
got to the station early to check out the truck and, if a late call came
in, take it so Greg and Chad could get off on time. This was an
arrangement the Medic 2 crews shared, and it worked well for them. As Adriane checked out the D cylinders and M tank, she said
offhandedly, “Better be sure we have plenty of Os. We’re due for a chest
pain call.” “Watch your mouth,” said Larry, grinning as he tossed her
the last of the Twinkies he’d saved. “You know what happens when you say
things like that.” Twenty minutes later they were at the home of Doris, one of their
regular patients, a 64-year-old type 2 diabetic who was, in fact,
experiencing chest pain she described as 5 on a scale of 0–10. While Larry attached the 12-lead, Adriane noted the pulse
oximeter read 97% on room air, so she put Doris on a non-rebreather mask
and turned the oxygen on at 15 liters per minute. “You can’t have
enough of this good stuff,” she said. “Let’s get that sat up to 100% for
those heart cells.” After giving an aspirin, starting an IV and giving a squirt of
nitroglycerin, they transported Doris to the nearby Level III hospital,
where she went immediately to the cath lab, got a stent in her right
coronary artery, went to the CCU and eventually returned home three days
later, feeling great. “Good job, folks,” Dr. Chutney said at the chart review the next
week, “but here’s something I need to pass along to you: We don’t do 15
liters per minute by non-rebreather for routine chest pain patients
anymore.” “Why?” said Adriane. “In my book it says not to worry about
problems from too much oxygen, that they only develop after several days
of more than 50% inspired oxygen delivered at higher-than-normal
pressures.” “What book are you reading from, Adriane?” asked Dr. Chutney. “From my Orange Book,” said Adriane, “Emergency Care and Transportation of the Sick and Injured, seventh edition, from my EMT class back in 2000.”
The Problem
In 2000 that was what we were taught about oxygen therapy for
patients with chest pain. But times have changed. We now know that while
some oxygen may be good, more is not necessarily better.
We have always known that oxygen is necessary for all animal life,
and that lack of oxygen damages tissues. It is beyond argument that
patients who are hypoxic must receive supplemental oxygen. What we’ve
not always known is that too much oxygen can harm patients in a number
of ways.
One is through reactive oxygen species (ROS), often called free
radicals. A radical is an atom that has one or more unpaired electrons.
Oxygen has two unpaired electrons that make it susceptible to radical
formation. When ROS form in cells, damage can occur. Hypoxic cells are
greatly susceptible to ROS. These can damage tissues throughout the
body, but of particular concern are lung, heart and brain tissues. Not
all radicals are bad, and the role of radicals is far beyond the scope
of this article, but we know that damage to the plasma membranes,
mitochondria and endomembrane systems by ROS is significant.
High oxygen concentrations can also cause atelectasis. Air is about
21% oxygen and 79% nitrogen. The alveoli depend on nitrogen to maintain
surfactant production and alveolar patency; when high concentrations of
oxygen are administered, oxygen may “wash out” nitrogen and leave the
alveoli susceptible to a lack of gas as oxygen diffuses into the blood,
causing them to collapse. This “washout” may be desirable temporarily in
patients being preoxygenated for rapid- or delayed-sequence intubation,
but over time atelectasis may occur, and this is not good. Once
intubation is accomplished, a natural mixture of gases must be allowed
to reconstitute in the lungs to avoid collapse of alveoli and
atelectasis. There is little to be gained by achieving an oxygen
pressure of greater than 100 mmHg.
Trauma Patients
Over the last 20 years we’ve been in the
habit of giving high-flow oxygen to just about everybody. Every trauma
patient gets oxygen at 15 lpm by non-rebreather mask, regardless of
their blood oxygen saturation. What many do not realize is that this was
taught not because it was beneficial, but because it was considered an
acceptable risk when time limitations necessitated deletion of much of
the medical theory during the 1994 revision of the EMT-Basic curriculum.
Everyone was taught to deliver high-flow oxygen by non-rebreather
without understanding why it was beneficial…or potentially harmful.
There is no medical evidence to support this practice unless the patient
is hypoxic or in shock.
In 2004, Tulane MDs Zsolt Stockinger and Norman McSwain monitored
5,090 trauma patients not requiring assisted ventilation to see whether
supplemental oxygen improved their outcomes. The results showed those
who received oxygen did no better or worse than those who did not. The
authors concluded supplemental oxygen does not improve survival in
traumatized patients who are not in respiratory distress.1
Chest Pain Patients
It has been our traditional practice to give high concentrations of
oxygen to patients with chest pain and MI, for reasons no better than
“this is how we’ve always done it.” As Israeli physician Chaim Lotan
said at a conference in 2011, “We have been brainwashed into using
oxygen” even though recent data suggests it has harmful effects that are
mediated primarily by coronary artery vasoconstriction. “Before I
started looking into the data,” Lotan said, “I didn’t understand how
much damage we were causing by giving oxygen.”2
In fact, it is true that 100% oxygen given by non-rebreather reduces
coronary artery flow by 30% after 5 minutes. It also reduces the effects
of vasodilators such as nitroglycerin.3
This is not exactly a result we’d desire while treating a patient
with coronary artery disease. For this reason, the American Heart
Association’s emergency cardiac care guidelines have, since 2010,
recommended as follows: There is insufficient evidence to support
[oxygen’s] routine use in uncomplicated ACS. If the patient is dyspneic,
hypoxemic or has obvious signs of heart failure, providers should
titrate therapy, based on monitoring of oxyhemoglobin saturation, to
≥94% (Class I, LOE C).4
In a Cochrane review of the literature, researchers in New Zealand
led by Meme Wijesinghe found that, although evidence is limited, it
suggests that routine use of high-flow oxygen in uncomplicated MI may
result in a greater infarct size and possibly increase the risk of
mortality.5 These authors concluded it is well-established
that arterial oxygen tension is a major determinant of coronary artery
blood flow and that high-flow oxygen therapy can cause a reduction in
cardiac output and stroke volume. They concluded there is insufficient
evidence to support the routine use of high-flow oxygen in the treatment
of uncomplicated MI, and that it may increase mortality.
Stroke Patients
Stroke patients should be managed similarly. Administer supplemental
oxygen to stroke patients who are hypoxemic or when oxygen saturations
are not obtainable; the goal is to maintain a saturation of 94% or
greater.
COPD Patients
The role of oxygen in chronic obstructive pulmonary disease (COPD)
patients has been debated for decades. Issues such as a theoretical
“hypoxic drive” in patients with COPD and chronic hypercarbia have led
to controversies over how much oxygen to give them. While hypoxia must
be corrected quickly when it exists, the definition of hypoxia in terms
of oxygen saturation has been unclear. For example, a normal person
without a respiratory condition breathing room air will usually have a
saturation varying from 97%–99%, depending on tidal volume and other
normal respiratory variances. It is almost impossible to achieve 100%
saturation by breathing room air. We know a saturation of 90% correlates
to approximately 60 mmHg pressure, and that is the normal threshold of
respiratory distress. However, COPD patients may be accustomed to less
saturation, and they typically do well at 88%–92%.
In a study of 405 patients in Australia published in 2010, Dr.
Michael Austin and colleagues compared the outcomes of COPD patients who
were given standard high-flow oxygen treatment with those given
titrated oxygen treatment by paramedics. Titrated oxygen treatment
reduced mortality compared with high-flow oxygen by 58% for all
patients.6
In a 2012 study of prehospital noninvasive
ventilation in patients with pulmonary edema and/or COPD, asthma and
pneumonia, a team led by Dr. Bryan Bledsoe found that use of CPAP with a
low oxygen percentage (FiO2) of 28%–32% was highly effective
in treatment of respiratory emergencies by medics. Since most CPAP
setups deliver 100% oxygen, it may be worthwhile for services to explore
the value of using setups with a lower oxygen percentage.7
Post-Cardiac Resuscitation Patients
Finally, the role of oxygen after cardiac resuscitation must be
mentioned. At one time we attempted to push as much oxygen as possible
into cardiac arrest patients on the theory that myocardial oxygen
supplies were quickly dwindling, and that if we wanted to save people,
we had to replenish the missing oxygen. During arrest, and if we were
fortunate enough to get a return of spontaneous circulation, we bagged
patients as fast and hard as we could, thinking we were restoring oxygen
to ischemic cardiac and brain cells.
Now we know that while ischemia is responsible for most cases of
cardiac arrest, managing reperfusion of ischemic cardiac cells is more
complicated than we thought. Because of the role of ROS (free radicals),
we now understand that a flood of oxygen into previously ischemic
cardiac cells is harmful.
The latest post-cardiac arrest care guidelines from AHA recommend the following: Avoid excessive ventilation. Start at 10–12 breaths/min and titrate to target PetCO2 of 35–40 mmHg. When feasible, titrate FiO2 to minimum necessary to achieve SpO2 equal to or greater than 94%.8
Conclusion
In Adriane’s copy of Emergency Care and Transportation,
pulse oximetry was not even mentioned because it was not routinely
available on ambulances then. Now that we routinely monitor SpO2
for most patients and know what we do about the dangers of
hyperoxygenation, it makes sense to give only as much oxygen as the
patient requires.
In the early days of EMS, venturi masks were popular and routinely
used for COPD and cardiac patients. Following the 1994 revision of the
EMT National Standard Curriculum, these were largely abandoned because
it was felt high concentrations of oxygen were an acceptable risk, given
the curriculum’s time limitations. We may see a return of venturi masks
to EMS as we become more aware of the need to limit oxygen percentages
in our therapy.
In the past 20 years, the debate in oxygen therapy has largely been
confined to high-flow versus low-flow. Given the current research and
assessment tools available to us, it would seem the debate should shift
to low-flow versus no supplemental oxygen at all. We have the means to
titrate oxygen therapy to patients’ needs, and those needs most often
can be met by low-flow oxygen.
By no means do we suggest that patients who need oxygen be denied it.
Hypoxia must be corrected immediately. But you can have too much of a
good thing.
References
1. Stockinger ZT, McSwain NE Jr. Prehospital supplemental oxygen in
trauma patients: its efficacy and implications for military medical
care. Mil Med, 2004 Aug; 169(8): 609–12.
6. Austin MA, Wills KE, Blizzard L, Walters EH, Wood-Baker R. Effect
of high flow oxygen on mortality in chronic obstructive pulmonary
disease patients in prehospital setting: randomized controlled trial. BMJ, 2010 Oct 18; 341: c5462.
7. Bledsoe BE, Anderson E, Hodnick R, Johnson L, Johnson S,
Devendorf E. Low-fractional oxygen concentration continuous positive
airway pressure is effective in the prehospital setting. Prehosp Emerg Care, 2012 Apr–Jun; 16(2): 217–21.
8. Circulation, 2010; 122: S768–86.
William E. “Gene” Gandy, JD, LP, has been a paramedic and EMS
educator for more than 30 years. He has implemented a two-year associate
degree paramedic program for a community college, served as both a
volunteer and paid paramedic, and practiced in both rural and urban
settings and in the offshore oil industry. He has testified in court as
an expert witness in a number of cases involving EMS providers and
lectures on medical/legal aspects of EMS. He lives in Tucson, AZ.
Steven “Kelly” Grayson, NREMT-P, CCEMT-P, is a critical care
paramedic for Acadian Ambulance in Louisiana. He has spent the past 14
years as a field paramedic, critical care transport paramedic, field
supervisor and educator. He is a former president of the Louisiana EMS
Instructor Society and board member of the Louisiana Association of
Nationally Registered EMTs. He is a frequent EMS conference speaker and
author of the book En Route: A Paramedic’s Stories of Life, Death, and Everything In Between, and the popular blog A Day in the Life of an Ambulance Driver.
Prehospital topical hemostatic agents - A review of the current literature
Prehospital topical hemostatic agents – A review of
the current literature
PHTLS
Executive Committee
Lance
E. Stuke, M.D. MPH
Background:
The 7th edition PHTLS
textbook discusses the use of topical hemostatic agents which were are available
for prehospital use. Products come and go from the market so it is difficult to
remain current on all available products. Additionally, older products may
still be in use due to surplus, although they may not be commercially
available. Data on many of these
products is based primarily on military reports and very little data is
available on their use in the civilian prehospital setting. The vast majority
of these products have been researched and developed for use in the military
setting in Iraq and Afghanistan although some limited civilian data is also
available. At the time of printing of the 7th edition of PHTLS, only
Combat Gauze has been recommended by the Tactical Combat Casualty Care
Committee (COTCCC) for military use.
The
perfect hemostatic dressing does not exist. Ideally, the dressing should be
lightweight, easy to store, and able to be rapidly applied to a hemorrhaging
wound. It should be conformable to the wound, allowing the hemostatic agent to reach
areas of injury which are difficult to access with direct pressure (i.e. deep
groin wounds). The dressing should cause minimal local tissue destruction, be
easily removable from the wound, and not contain particles which can spread
systemically. Finally, the dressing must not be washed away by rapid bleeding
from high-flow blood vessels.
Manufacturers have tried various methods to
deliver hemostatic agents into bleeding wounds. Some products are packaged into
a granular form which can be poured directly into the wound. Others are
incorporated into a dressing or mesh which allows the provider to apply direct
pressure to the site of injury. This dressing can be formed either as a rigid
bandage, a small bag, or a gauze which must be unrolled prior to application.
Each method of preparation has distinct advantages and disadvantages depending
on the location and type of injury being treated.
Literature
and Product Review:
HemCon:
HemCon dressing (Hemorrhage Control Technologies, Portland, OR), is composed of
chitosan, a substance derived from arthropod skeletons. Chitosan dressings are
thought to function by mechanically sealing the wound and adhering to
surrounding tissue. HemCon is a dual-sided 4 x 4 inch rectangular bandage: a
chitosan-containing active side which must be placed directly on the wound and
a nonstick side which the provider uses to apply pressure. The efficacy of
HemCon depends entirely on the bandage adhering well to the wound, which is
difficult in wounds which aren’t flat and easily accessible. The bandage isn’t
flexible and can break when forced into a wound. It is best applied to flat,
superficial wounds which are easily accessible. HemCon has been studied in both
the military and civilian settings. The military demonstrated a 97% success
rate in controlling bleeding with HemCon.1,2 The civilian experience has been less
optimistic, controlling bleeding in 27 of 34 cases studied (79%). Of the seven
failures, six were felt to be due to user error, possibly due to less training by
civilian EMS providers in the proper use of the product.3 An
additional study using a complex groin injury model in swine noted an increase
in the rate of rebleeding and mortality between those treated with HemCon versus
QuikClot. The authors noted that
application of HemCon was more difficult than other agents and all failures of
HemCon were due to the bandage not adhering to the injured tissue to which it
was applied.4
As
previously noted, a disadvantage of the HemCon dressing is that it is
relatively non-conformable and difficult to pack into deeper wounds. ChitoFlex
is the latest development from HemCon Medical Technologies. It utilizes the
same chitosan-based hemostatic agent but packages it into a gauze form. This
allows the dressing to be packed into deep bleeding wounds for improved access
to the site of hemorrhage. ChitoFlex is available in several sizes, including
1”x3”, 3”x9”, and as a 3”x28” roll. In one study, ChitoFlex was found to be
equivalent, but not superior to QuikClot and Celox (a chitosan granule).5
WoundStat: WoundStat
was an FDA-approved mineral-based agent consisting of granular smectite, a
nonmetallic clay. When the granules were exposed to blood they absorbed water,
swelled, and formed a clay paste with strong adhesiveness to the surrounding
tissue. Initial studies were promising6,7,8 and it was used by the U.S. Army for a short
time. However, later data demonstrated that the granules could cause injury to
the blood vessels and make repair difficult. The granules were also shown to
enter the circulatory system and cause thrombosis in distal organs.9
Because of these potentially serious side effects, the U.S. Army announced in
April 2009 that WoundStat would no longer be used by their medical personnel.
QuikClot: QuikClot
(Z-Medica, Wallingford, CT) is a granular product consisting of kaolin, which
is a combination of inert minerals such as silicon, aluminum, magnesium, and
sodium found in volcanic rock. When placed in a bleeding wound, it absorbs
water thereby increasing the local concentration of clotting factors,
platelets, and red blood cells to stimulate clot formation. A byproduct of its
mechanism is a severe exothermic reaction, with heat generation of up to 70̊ C
(158o F). This heat generation causes local tissue destruction and
even burns. QuikClot has been studied in both the military and civilian sector,
with up to 92% effectiveness in stopping hemorrhage.10 QuikClot was
issued to U.S. soldiers in the Iraq and Afghanistan conflicts. Civilian use has
been by a wide range of providers, including EMT/firefighters, paramedics, and
police. Examples of civilian use include treatment of severe lacerations,
gunshot wounds to the neck and even hemodialysis catheter dislodgement. Trauma
surgeons have also used QuikClot for successful treatment of bleeding during
surgery in the chest, abdomen, and pelvis. QuikClot was noted to have two
significant weaknesses. Since it is a granular powder poured into a wound, it
had limited usefulness in high-pressure bleeding (i.e. femoral artery bleed) as
the granules were washed away by the bleeding before they were able to form a
clot. Furthermore, the heat generated from its use was associated with several burns.
QuikClot production
was stopped after development of several newer generation products. These newer
generation products have minimal heat production and are packaged both as
gauzes and in a bagged form. Currently Z-Medica sells QuikClot packaged in
2”x2” and 4”x4” gauze pads for use on superficial lacerations which don’t have
severe bleeding. QuikClot has also developed a small zeolite-impregnated pad
(QuikClot ACS+) and as a laparotomy pad (QuikClot Trauma Pad) for use by trauma
surgeons in the operating room for cases of severe bleeding during surgery.
This later product remains in the research phase and is not yet approved for
widespread use.
Combat GauzeTM is a 3”x4 yard long roll of nonwoven gauze
impregnated with kaolin. Combat Gauze has all the advantages of normal gauze
(easy application, flexible, large coverage area, and easily removable) with
the additional advantage of hemostatic function from the kaolin. It is designed
for packing into deep wounds which are actively bleeding (i.e. arterial injury
in the groin). Prehospital personnel can also use combat gauze as they would
any standard Kerlix gauze. Combat Gauze was recently compared to several newer
generation products, including the HemCon RTS, and found to be superior and had
no apparent side effects.11 A study from the Israel Defense Force
reviewed fourteen uses of Combat Gauze and noted a 79% success rate.12
The authors noted that in the three instances where Combat Gauze was
unsuccessful, the soldiers had such severe injuries that only surgical control
was successful. One of the three soldiers died from the severity of his wounds.
Currently, Combat Gauze is the only product endorsed by the Tactical Combat
Casualty Care Committee and they recommend it as first line treatment for
life-threatening hemorrhage on external wounds not amendable to direct pressure
and tourniquet placement.
A disadvantage
of most topical hemostatic agents is they require 2-5 minutes of direct
pressure to be effective. This amount of time is often not available during
care under fire situations seen in combat or during a mass casualty situation.
A study published in the Journal of Trauma compared Combat Gauze (used by the
U.S. military), Celox Gauze (used by the United Kingdom), and standard Kerlix
gauze.13 A 6mm side-wall injury was created in swine, 30 seconds of
free hemorrhage was allowed, and wounds were packed with one of the three
gauzes. The animals were resuscitated with Lactated Ringers to maintain
baseline mean arterial pressure. The authors noted no difference in success of
either dressing. The Kerlix gauze was packed faster than Combat and Celox
Gauze. There was no difference in survival, dressing success, or blood loss
between the three dressings. The authors note they were somewhat surprised by
this finding and note that in care under fire situations where tourniquet use
is not an option, standard gauze packed in a wound performed equally well to
Combat Gauze and Celox Gauze.
A study from the
Naval Medical Center in Portsmouth, VA compared several commercially available
topical hemostatic agents to the application of direct pressure with standard
gauze.14 The authors used a swine model with a severed femoral
artery and vein to simulate a high-velocity projectile injury with jagged
surrounding muscle. Combat Gauze, WoundStat, Celox-A, and ChitoFlex were
applied to the created injuries per the manufacturer recommendations. They were
then compared to each other and to standard gauze applied using direct
pressure. Manual pressure was held for 5 minutes and any bleeding occurring
after this was considered a failure of hemostasis. Primary outcome measures
were failure of initial hemostasis and the incidence of rebleeding. Secondary
measures included total blood loss, amount of rebleeding, and survival.
WoundStat performed more poorly than Celox-A in achieving initial hemostasis
and in the incidence of rebleeding. Surprising to the authors, standard gauze
and direct pressure performed equally as well as the 4 commercially available
topical hemostatic agents. There were no significant differences in failure of
initial hemostasis, rebleeding, or death between standard gauze and the other
agents.
Summary:
- Numerous
topical hemostatic products have been developed and released onto the market.
- Some of these
products have since been discontinued, while others are widely used.
-Economic and
medical considerations continue to make this a rapidly evolving and growing area of prehospital care. It is
important for the EMS provider to remain cognizant
of these products and their advantages, disadvantages, and complications as they continue to evolve.
- Recent data
suggests direct pressure with standard gauze may be equally effective as commercially available hemostatic agents.
Providers should consider this when attempting
to control hemorrhage. Principles of adequate direct pressure and wound packing continue to be the
cornerstone of controlling severe traumatic bleeding from penetrating extremity wounds.
PHTLS
Recommendation: Topical
hemostatic agents may be used to control hemorrhage occurring in sites not
amenable to tourniquet placement and which cannot be controlled by direct
pressure alone.
Bibliography
1.Achneck
HE, Sileshi B, Jamiolkowski RM, et al. A comprehensive review of topical
hemostatic agents: Efficacy and recommendations for use. Annals of Surgery 2010; 251: 217-228.
2.Mabry
R and McManus JG. Prehospital advances in the management of severe penetrating
trauma. Crit Care Med. 2008:36(7);S258-266.
3.Brown
MA, Daya MR, Worley JA. Experience with chitosan dressings in a civilian EMS
system. J Emerg Med. 2009;62:239-243.
4.Kozen
BG, Kircher SJ, Henao J, et al. An alternative hemostatic dressing: comparison
of CELOX, HemCon, and QuikClot.Acad Emerg
Med. 2008; 15:74-81.
5.Devlin
JJ, Kircher S, Kozen BG, et al. Comparison of ChitoFlex, CELOX, and QuikClot in
control of hemorrhage. J Emerg Med.
2009 Apr 1 (Epub ahead of print).
6.Ward
KR, Tiba MH, Holbert WH, et al. Comparison of a new hemostatic agent to current
combat hemostatic agents in a swine model of lethal arterial hemorrhage. J Trauma. 2007;63:276-284.
7.Kheirabadi
BS, Edens JW, Terrazas IB, et al. Comparison of new hemostatic granules/powders
with currently deployed hemostatic products in a lethal model of extremioty
arterial hemorrhage in swine. J Trauma. 2009;66:316-328.
8.Arnaud
F, Parreno-Sadalan D, Tomori T, et al. Comparison of 10 hemostatic dressings in
a groin transaction model in swine. J
Trauma. 2009;67:848-855.
9.Bheirabadi
BS, Mace JE, Terrazas IB, et al. Safety evaluation of new hemostatic agents,
smectite granules, and kaolin-coated gauze in a vascular injury wound model in
swine. J Trauma. 2010;68:269-278.
10.Rhee
P, Brown C, Martin M, et al. QuikClot use in trauma for hemorrhage control:
case series of 103 documented uses. J
Trauma. 2008;64:1093-1099.
11.Kheirabadi
BS, Scherer MR, Estep JS, et al. Determination of efficacy of new hemostatic
dressings in a model of extremity arterial hemorrhage in swine. J Trauma. 2009;67:450-460.
12.Ran
Y, Hadad E, Daher S, et al. QuikClot Combat Gauze Use for Hemorrhage Control in
Military Trauma: January 2009 Israel Defense Force Experience in the Gaza Strip
– A Preliminary Report of 14 Cases. Prehop
Disaster Med 2010;25(6):584-588.
13.Watters
JM, Van PY, Hamilton GJ, et al. Advanced Hemostatic Dressings Are Not Superior
to Gauze for Care Under Fire Scenarios. J
Trauma. 2011;70:1413-1419.
14.Littlejohn
LF, Devlin JJ, Kircher SS, et al. Comparison of Celox-A, ChitoFlex, WoundStat,
and Combat Gauze Hemostatic Agents Versus Standard Gauze Dressing in Control of
Hemorrhage in a Swine Model of Penetrating Trauma. Acad Emerg Med. 2011:18(4);340-350.